

Early pregnancy often becomes defined by numbers. A blood result arrives, you compare it with the last one, and the question remains: what does this mean for this pregnancy?
Receiving a number and receiving an answer are not always the same thing. A result may help your care team decide what to check next without settling everything you want to know.
Understanding hCG levels in early pregnancy means understanding both the information and its limits. The aim is to make the conversation with your clinician clearer, including why another blood test or scan may be needed.
What hCG blood tests measure
Human chorionic gonadotropin, or hCG, is a hormone produced by developing placental tissue during pregnancy. It is often called the pregnancy hormone because pregnancy tests look for it. Detecting it does not, by itself, show where a pregnancy is developing or whether it will continue.
There are two different kinds of result:
- Qualitative: whether hCG is detected, usually reported as positive or negative.
- Quantitative: the measured amount of hCG in the blood sample, reported as a number with units.
MedlinePlus explains that blood tests can be either qualitative or quantitative. A blood test is not automatically a numerical test. If you are expecting a value to compare with a previous result, it is reasonable to ask which test was ordered.
A quantitative test allows clinicians to compare measurements over time. That can contribute to follow-up when there are questions about an early pregnancy. It does not replace the rest of the assessment or establish that everyone needs serial blood testing.
Home urine tests answer a different question. They detect hCG rather than supplying the quantitative blood measurements used in this kind of follow-up. They cannot replace a blood test your team has arranged. The FDA notes that testing too early can produce a negative result despite pregnancy; follow the instructions for the test you use rather than assuming detection is certain on a particular day.
The useful distinction is between detecting the hormone and measuring it for a clinical purpose. Neither kind of result supplies all the information needed to assess a pregnancy.
What one hCG result can and cannot tell you
A single result has information. It records the measured concentration in that sample and may provide a starting point for comparison. But a concentration is not a complete account of what is happening.
The NICE guidance on early-pregnancy assessment separates the role of hCG from the assessment of pregnancy location. A number cannot establish location by itself. Your clinician interprets it alongside the reason for testing, symptoms, dates and any scan findings.
Timing matters in more than one way. There is the date and time the sample was collected, and there is the estimated stage of pregnancy. If ovulation happened later than assumed, the dating may be less certain than a calendar suggests. That is a reason to discuss the dates, not a way to diagnose the meaning of a low result at home.
Laboratory context matters too. MedlinePlus notes that reference ranges can vary between laboratories. Keep the report with its units and collection details, rather than copying just the number into a message. If tests were performed by different laboratories, tell your team so they can consider that when comparing them.
Published ranges can provide broad context, but they are not a personal pass/fail system. The table below uses gestational age.
Typical hCG Ranges in Early Pregnancy
| Gestational age | Reference hCG range |
|---|---|
| 3 weeks | 5–72 mIU/mL |
| 4 weeks | 10–708 mIU/mL |
| 5 weeks | 217–8,245 mIU/mL |
| 6 weeks | 152–32,177 mIU/mL |
| 7 weeks | 4,059–153,767 mIU/mL |
| 8 weeks | 31,366–149,094 mIU/mL |
| 9 weeks | 59,109–135,901 mIU/mL |
| 10 weeks | 44,186–170,409 mIU/mL |
Important: These are broad reference ranges, not targets or diagnostic cutoffs. hCG levels can vary widely, and reference ranges may differ between laboratories. A value inside or outside one of these ranges cannot by itself determine whether a pregnancy is viable or where it is located.
These ranges overlap widely and do not account for every detail of your dates, testing or assessment. Laboratory ranges may differ. Another person’s result, even from what seems to be the same pregnancy week, cannot determine your outcome. Nor should a value that fits a published range override concerning symptoms or clinical assessment.
What an hCG result can tell you / what it cannot tell you
| Can contribute to | Cannot establish by itself |
|---|---|
| Understanding the measured amount of hCG in that sample. | Where the pregnancy is located. |
| Assessing change when compared with another timed sample. | Whether the pregnancy is viable. |
| Information used to decide the next clinical follow-up step. | Whether medical follow-up is finished. |
Rather than asking a single result to settle every question, ask which question it helps answer. Your team may be using it as a baseline, comparing it with an earlier sample, or interpreting it alongside a scan. Knowing its purpose helps explain why the same number cannot mean the same thing in every situation.
Why clinicians compare results over time
When interpreting hCG levels in early pregnancy, clinicians compare timed measurements to assess change. The starting value and the time between samples both matter. A result collected later is not directly equivalent to one collected sooner, even if the numbers look similar.
The familiar doubling question comes from trying to describe this change. However, there is no universal timetable on which every viable pregnancy’s hCG must double. Replacing that expectation with one different percentage would create another misleading rule.
In a 2016 study, Barnhart and colleagues modeled hCG rises in symptomatic patients whose pregnancies were ultimately confirmed to be viable and intrauterine. The modeled rise varied with the starting concentration. These were estimates from a particular population, not a guarantee for an individual pregnancy or a way to locate it.
Research also illustrates the limits of comparing someone with an expected curve. Morse and colleagues studied patients with a pregnancy of unknown location and found that serial hCG patterns alone could misclassify pregnancy outcomes. Their findings support using clinical judgment and other information alongside the measurements.
This is why a minimum rise described in a study should not become a personal pass/fail line. Being above it cannot promise a healthy outcome; being below it cannot independently establish a diagnosis. The research can inform clinical assessment without becoming a home scoring system.
Repeat testing also has a purpose and a schedule. NICE describes timed sampling within a clinician-managed follow-up pathway, rather than a testing routine for every pregnancy. Ask when your next sample should be taken and why that interval was chosen. Do not assume someone else’s blood-draw schedule applies to you.
It can help to keep previous reports together so your clinician has the actual sequence, including collection times. That is different from trying to calculate a verdict yourself. If a planned appointment or blood draw becomes difficult to attend, contact the team about the plan rather than quietly changing the interval and interpreting the next result as though nothing changed.
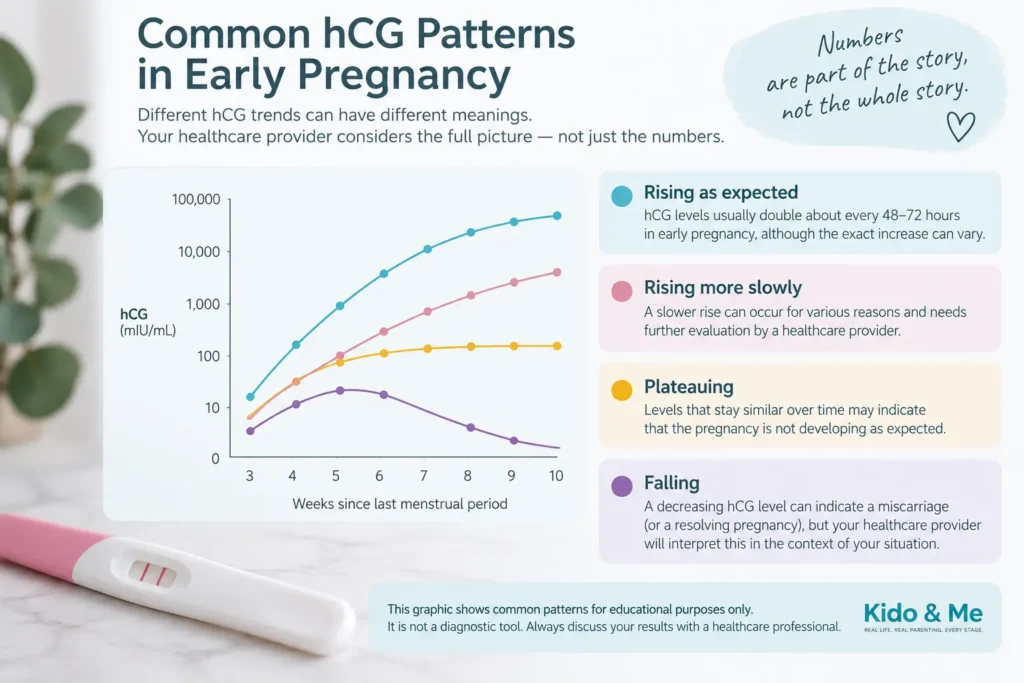
What rising, slow, plateauing and falling hCG can mean
These descriptions refer to patterns in measurements. They can help frame the next clinical question, but they are not interchangeable with diagnoses. What has already been established about the pregnancy matters alongside the direction of change.
Rising hCG
A rise means more hCG was measured in the later sample. It can contribute information about pregnancy progression, but it does not prove that the pregnancy is inside the uterus, viable or certain to have a healthy outcome.
NICE retains the possibility of ectopic pregnancy even in its pathway for a substantial rise. That distinction matters when the location has not yet been established. A favorable-looking trend does not answer a question that requires other evidence.
You may understandably feel encouraged when a result rises. The clinical question is what that rise contributes in your situation. Has the team identified the location? Are they waiting for a scan to clarify something? Does the result change the next appointment, or does the agreed plan continue?
A clinician saying that a result is encouraging is not necessarily saying that the assessment is complete. Ask what remains to be checked rather than trying to translate a reassuring word into a guarantee.
The next step may still involve follow-up. That does not make the rise meaningless; it means the result has answered only part of the question. Continue to report symptoms rather than treating the direction of the numbers as permission to overlook a change in how you feel.
Slow-rising hCG
A slower-than-expected rise may lead your clinician to seek more information. It does not automatically mean miscarriage or ectopic pregnancy, and failure to double is not a diagnosis.
The meaning depends on the measurements being compared, their timing and the rest of the assessment. The Morse study’s findings on classification errors are relevant here: a curve alone does not reliably settle every pregnancy’s outcome.
Dating uncertainty needs careful handling. Later ovulation may change expectations about how far along a pregnancy is or how an isolated value compares with the assumed dates. It does not automatically explain every pattern between repeated samples. The elapsed time between two blood draws is a different piece of information from the estimated date of ovulation.
Tell the clinician if your dates are uncertain, but do not use that uncertainty to dismiss a pattern they want to investigate. Equally, you do not need to decide what caused the slower rise before contacting them.
If you are told the rise is slower than expected, a useful question is what additional information the team needs. They can explain whether the next assessment is intended to examine the trend, clarify the scan findings or address symptoms. The phrase “slow-rising” describes a concern to evaluate; it should not leave you having to assign yourself a diagnosis or decide how much follow-up is enough.
Plateauing hCG
A plateauing pattern means there is little change over repeated measurements. It does not require every result to be identical. The team considers the amount of change, the sampling interval and the wider clinical picture rather than relying on one universal plateau cutoff.
Plateauing hCG can leave important questions unresolved. It is not another name for biochemical pregnancy, and it does not establish ectopic pregnancy. NICE includes patterns with limited change among those needing clinical review; the review provides context the label alone cannot.
For a reader, “little change” may sound as though there is nothing new to discuss. In follow-up, however, that pattern can itself be information your clinician needs to consider. It does not mean that waiting indefinitely is the plan.
Ask what the team is trying to clarify and what happens next if uncertainty continues. A plateau should not leave you responsible for inventing a testing schedule. If symptoms appear or worsen while you are waiting, seek advice sooner rather than assuming that an almost unchanged value means an unchanged clinical situation.
Falling hCG
Falling values in an assessed early pregnancy may indicate that the pregnancy is not continuing. That can be difficult news to hear, particularly if earlier results were rising. Your team needs to explain what the decline means alongside the other findings.
NICE’s guidance describes a falling pattern as making continuation unlikely in a particular follow-up context, without treating that alone as confirmation. A decline also does not establish where the pregnancy was located.
Those are separate questions. Evidence that a pregnancy may not be continuing is not automatically evidence that it was inside the uterus. If the location is unresolved, falling hCG does not, by itself, exclude ectopic pregnancy or mean follow-up is finished.
If your clinician has established an early loss and described it as a biochemical pregnancy, information about that experience may help. Do not apply that label solely because a result fell or a scan did not show a pregnancy.
Ask what follow-up remains and how your team will determine when it is complete. A lower result should not make you reluctant to report pain, bleeding or other changes. This discussion concerns early-pregnancy assessment; it is not a rule that every decrease in hCG at every stage of pregnancy means a loss.
How hCG and ultrasound fit together
Understanding hCG levels in early pregnancy also means knowing what ultrasound contributes. A hormone concentration is not an image of pregnancy location. Ultrasound can help answer questions that a blood measurement cannot, while the blood result may contribute to interpreting what is happening over time.
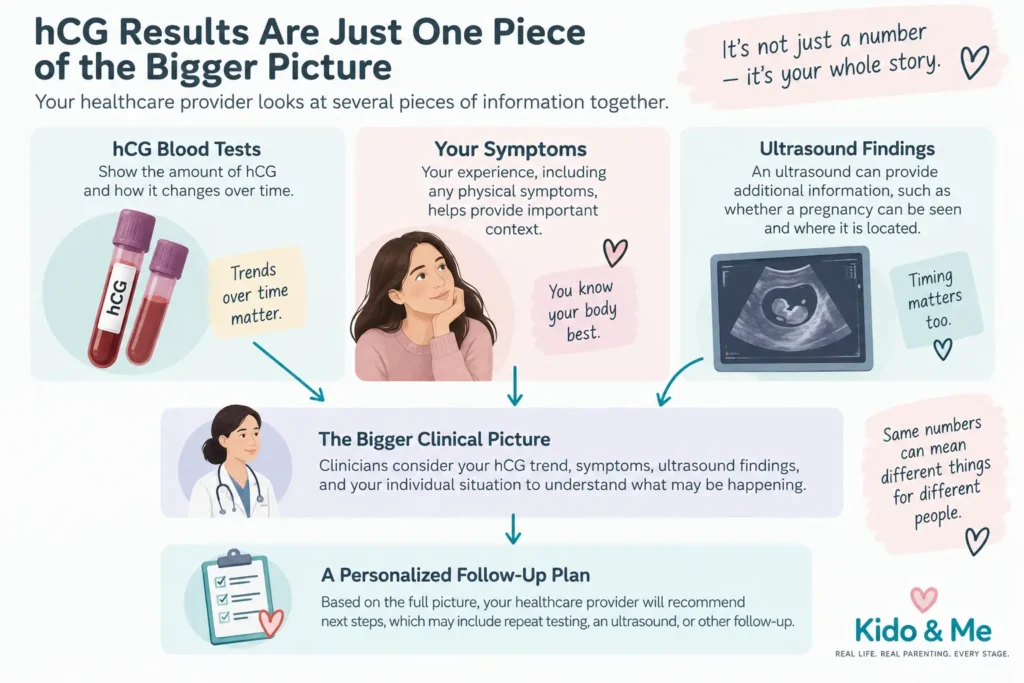
NICE recommends ultrasound as part of assessing pregnancy location. Scan findings are considered with symptoms, dates, examination where appropriate and test results. There is no universal hCG number you can use at home to decide what must be visible.
An early scan can be inconclusive. That is not the same as confirming that there is no problem, and an empty-looking uterus does not by itself establish an ectopic pregnancy. Sometimes further assessment is needed before the findings can be interpreted more clearly.
A positive pregnancy test with no pregnancy yet identified on ultrasound may be described as a pregnancy of unknown location, or PUL. It describes what remains uncertain, not a final diagnosis. The RCOG explanation of PUL and investigation describes assessment using clinical features, blood results and scans together.
It is useful to distinguish “the scan has not identified the location” from “the scan has established a diagnosis.” Ask which description applies and what the next assessment is intended to clarify. You do not need to interpret the images yourself.
A further blood draw after an inconclusive scan is not a substitute for every question the scan could answer. Likewise, having had a scan does not make later symptoms irrelevant. The care plan should account for what is known now and what still needs attention. If something changes between appointments, contact the team rather than relying on the earlier scan or a previous hCG result to answer the new concern.
Making follow-up more understandable
Another result may add information without giving closure. A blood draw or scan can help the team choose the next step even when the overall answer remains uncertain. It is reasonable to ask them to explain that step in language you can use after the appointment.
In my own experience, repeated hCG results did not always bring a clear answer. I kept waiting for the next result while ultrasounds remained inconclusive. The testing became part of everyday life, but receiving another number did not mean I knew what would happen next.
That is a personal account of uncertainty, not clinical evidence or a confirmed ectopic diagnosis. Your assessment and follow-up may be different.
The practical questions are often straightforward:
Questions to ask about your hCG results
- What is this test intended to clarify? Ask which uncertainty the team is investigating.
- What does this result change about my follow-up? Clarify whether the next step has changed or remains the same.
- When and how will I receive the next result? Ask who will explain it and whom to contact if the expected communication does not arrive.
- Who should I contact if symptoms change? Include arrangements outside normal office hours.
- Does using a different laboratory affect how the results are compared? Let the team know where each sample was taken and keep the reports available.
You do not need to arrive with a spreadsheet or a theory about the diagnosis. A short note with your questions, the appointment details and any symptoms you want to describe may be enough to help the conversation.
Follow-up also has to fit around ordinary responsibilities. If an appointment means finding childcare or rearranging work, tell the team about difficulties attending. You might ask someone to cover a school pickup or accompany you, without feeling obliged to explain every result. These are options for practical support, not extra tasks you must complete.
Before ending a call or leaving an appointment, check that you understand what is expected next and who is responsible for arranging it. If the answer is “we need another result,” you can still ask what that result is intended to contribute.
NICE emphasizes reassessment when symptoms change, regardless of previous results. A communication plan helps you know whom to reach; it does not make waiting through concerning symptoms appropriate.
Frequently asked questions
Does being over 35 change how hCG is interpreted?
Age may be statistically associated with differences in hCG curves. In the Barnhart study, some patient-factor differences were statistically significant without establishing a separate clinical rulebook. The reviewed NICE pathway does not provide distinct over-35 hCG thresholds.
That does not mean age has no relationship to pregnancy care. It means age alone does not supply a different home interpretation rule or establish that everyone over 35 needs serial testing. Ask how your individual history affects the care being recommended, rather than assuming an age label changes what a number can diagnose.
Does a high hCG result mean twins?
No. One high result cannot establish twins or a specific diagnosis. MedlinePlus lists more than one possible association with higher values; a list of possibilities is not a way to identify the explanation for your result.
Your clinician considers the value in context, including dates and scan findings. Ask what “high” means in the conversation about your own assessment and whether anything further needs checking. A number above someone else’s does not establish a multiple pregnancy, and “higher” should not be read as a promise of a better outcome.
What You Need to Know
- One hCG value provides information, but not a complete diagnosis.
- Trends need clinical context, including the starting value, sampling interval and other findings.
- hCG alone cannot establish pregnancy location or guarantee a healthy outcome.
- Falling values do not automatically exclude ectopic pregnancy or finish follow-up.
- Symptoms can require assessment despite a seemingly reassuring result.
When discussing hCG levels in early pregnancy, ask what the current result changes and how to contact your care team if symptoms change. Keep the agreed follow-up plan clear, and seek appropriate care for concerning symptoms rather than waiting for another number.
References
- NICE NG126: Diagnosis of viable intrauterine pregnancy and of tubal ectopic pregnancy.
- MedlinePlus: Pregnancy Test.
- MedlinePlus: HCG blood test — quantitative.
- FDA: Pregnancy.
- NHS: Ectopic pregnancy symptoms.
- RCOG: Ectopic pregnancy.
- Barnhart et al. (2016): Differences in Serum Human Chorionic Gonadotrophin Rise in Early Pregnancy by Race and Value at Presentation.
- Morse et al. (2012): Performance of hCG curves in women at risk for ectopic pregnancy: exceptions to the rules.








